- Tu carrito está vacío
- Continuar comprando



Rango de precios: €200 por €1,200
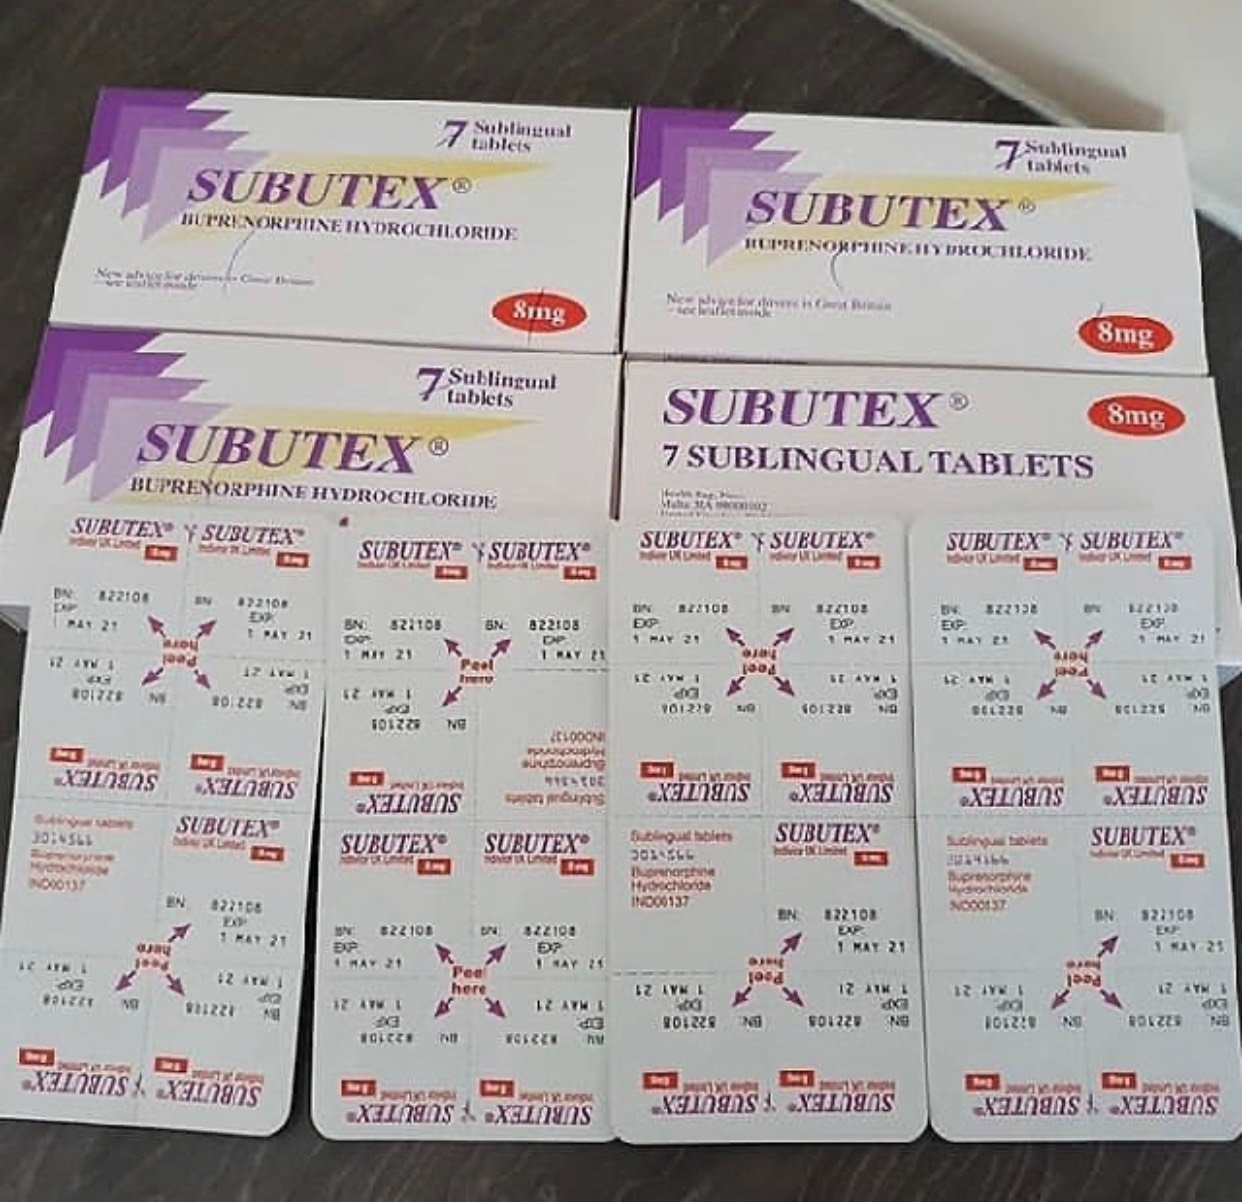
riginally developed in the late 1960s by Reckitt & Colman and approved as an analgesic before becoming an international standard for medication-assisted treatment (MAT), Subutex represents the prototypical sublingual buprenorphine formulation. Unlike combination formulations (such as Suboxone, which incorporates naloxone in a 4:1 ratio to deter intravenous diversion), Subutex contains only buprenorphine hydrochloride. It is clinically utilized during the fragile induction phase of OUD stabilization, in pregnant or lactating patients where naloxone exposure is clinically avoided, and in individuals with documented adverse reactions or allergies to naloxone.
Pharmaceutical Profile & Physical Architecture
Active Pharmaceutical Ingredient: Buprenorphine hydrochloride (formulated as 2 mg or 8 mg of free buprenorphine base equivalent).
Chemical Family: Thebaine-derived orvinol derivative belonging to the semi-synthetic morphinan/bridged morphinan family.
Molecular Formula & Mass: $\text{C}_{29}\text{H}_{41}\text{NO}_4 \cdot \text{HCl}$ | 467.64 g/mol (freebase), 504.10 g/mol (hydrochloride salt).
Dosage Form & Physical Presentation:
2 mg Formulation: Small, white to off-white, oval or round compressed sublingual tablet debossed with manufacturer-specific identification codes (e.g., an alphanumeric sword or alphanumeric press markings like “B2”).
8 mg Formulation: Larger white to off-white oval or hexagonal sublingual tablet debossed with strength identifiers (e.g., “B8”).
Excipients: Formulated with citric acid monohydrate, anhydrous sodium citrate, lactose monohydrate, mannitol, maize starch, povidone, and magnesium stearate, engineered to dissolve sublingually within 2 to 10 minutes.
Pharmacodynamics & Multi-Receptor Profile
High-Affinity Partial Agonism at $\mu$-Opioid Receptors ($\mu$-OR): Buprenorphine binds to human $\mu$-opioid receptors with exceptionally high binding affinity ($K_i \approx 0.2\text{–}0.7\text{ nM}$) and exhibits a remarkably slow receptor dissociation off-rate ($t_{1/2\text{ dissociation}} > 1\text{ hour}$). As a partial agonist, its intrinsic activity at the receptor is lower than full agonists (morphine, methadone, oxycodone, fentanyl), producing a distinct pharmacological ceiling effect for euphoria and respiratory depression.
$\kappa$-Opioid Receptor ($\kappa$-OR) Antagonism: Acts as a potent competitive antagonist at $\kappa$-opioid receptors. By blocking dynorphin-mediated $\kappa$-OR signaling in the nucleus accumbens and amygdala, buprenorphine exerts therapeutic anxiolytic and antidepressant effects, mitigating the dysphoria and anhedonia typical of post-acute opioid withdrawal.
$\delta$-Opioid Receptor ($\delta$-OR) & Nociceptin Receptor Modulation: Acts as a weak antagonist or partial agonist at $\delta$-opioid receptors and an agonist at opioid-receptor-like 1 ($\text{ORL-1}$ / nociceptin) receptors at elevated clinical concentrations.
Pharmacokinetics & Sublingual Biotransformation
Absorption & Route-Dependent Bioavailability: Undergoes extensive, near-complete first-pass hepatic metabolism and intestinal wall degradation if swallowed, resulting in negligible oral bioavailability ($<10\%$). Administered strictly sublingually, it bypasses initial hepatic clearance to achieve an absolute systemic bioavailability of approximately 30% to 55%. Peak plasma concentrations ($C_{\max}$) are reached within 40 to 90 minutes post-dissolution.
Distribution & Protein Binding: Highly lipophilic molecule with an extensive volume of distribution ($V_d \approx 188\text{ to }430\text{ L}$), rapidly distributing across the blood-brain barrier into lipid-rich central nervous system tissues. Approximately 96% bound to plasma proteins, predominantly $\alpha$– and $\beta$-globulins.
Hepatic Biotransformation (Phase I & II):
CYP3A4 N-Dealkylation: Extensively biotransformed in the liver via cytochrome P450 3A4 to norbuprenorphine, its primary active metabolite. Norbuprenorphine is a full $\mu$-opioid agonist but possesses low lipophilicity, limiting its ability to cross the intact blood-brain barrier under standard conditions.
Glucuronidation (Phase II): Both buprenorphine and norbuprenorphine undergo substantial Phase II conjugation via UDP-glucuronosyltransferases ($\text{UGT1A1}$ y $\text{UGT2B7}$) to form pharmacologically inactive glucuronide conjugates.
Elimination Kinetics: Displays an extended terminal elimination half-life ranging from 24 to 42 hours, governed by its prolonged storage in fatty tissues and slow dissociation from target receptors. Elimination is predominantly fecal/biliary (~70%, primarily as unconjugated buprenorphine and norbuprenorphine) with renal excretion accounting for roughly 30% (mainly as glucuronidated metabolites).
Clinical Indications & Induction Guidelines
Therapeutic Application: Indicated for the induction and maintenance treatment of opioid dependence within a comprehensive framework of medical, social, and psychological support.
The Induction Protocol & Objective Withdrawal: Because buprenorphine possesses higher binding affinity than most full agonists, administering it to a patient with circulating full agonists will result in the immediate displacement of those agonists, causing precipitated opioid withdrawal.
Clinical Requirement: Therapy must only be initiated when the patient exhibits objective, physical signs of moderate opioid withdrawal (quantified via a validated tool such as the Clinical Opiate Withdrawal Scale [COWS], typically requiring a score $>12$).
Timing Benchmarks: Generally 12 to 24 hours after the last dose of short-acting opioids (heroin, immediate-release oxycodone), and 24 to 72+ hours following cessation of long-acting full agonists (methadone, sustained-release formulations).
Administration Mandate: The tablet must be placed under the tongue and allowed to dissolve completely. Patients must be instructed not to chew, swallow, consume food, or drink liquids during dissolution, as this significantly diminishes systemic absorption.
Safety Considerations, Boxed Warnings, & Drug Interactions
Lethal CNS Depression with Benzodiazepines: The co-administration of buprenorphine with benzodiazepines, sedatives, or alcohol carries a Boxed Warning for profound sedation, respiratory arrest, coma, and death. While buprenorphine displays a ceiling effect on respiratory depression when taken alone, concurrent GABAergic modulation bypasses this protective mechanism.
Severe Precipitated Withdrawal Risk: Administration prior to the clearance of full $\mu$-agonists induces an acute, violent withdrawal syndrome characterized by diaphoresis, rhinorrhea, severe abdominal cramping, emesis, diarrhea, hypertension, tachycardia, and intense psychological distress.
Hepatic Toxicity: Cases of cytolytic hepatitis, severe hepatic transaminase elevations, and hepatic failure have been documented. Baseline hepatic profiles (AST, ALT, bilirubin) and ongoing surveillance are required, particularly in patients with viral hepatitis (HBV/HCV co-infection) or pre-existing liver impairment.
Diversion & Injection Abuse Vulnerability: Because Subutex lacks the naloxone deterrent present in Suboxone, crushed tablets suspended in water present a high risk of intravenous injection abuse among individuals with physical dependence. Intravenous administration of crushed tablet excipients introduces severe risks of local tissue necrosis, endocarditis, and pulmonary microemboli.
Analytical Screening & Forensic Identification
Presumptive Colorimetric Screening:
Marquis Reagent: Unreactive or produces an extremely slow, faint pinkish-red to pale violet hue, distinguishing buprenorphine from morphine, codeine, or heroin (which turn deep purple-black rapidly).
Mecke Reagent: Produces a slow, muted transition to brown or green-brown.
Froehde Reagent: Typically yields a slow, distinct shift toward blue-green.
Instrumental Profiling & Chromatography:
Liquid Chromatography-Tandem Mass Spectrometry (LC-MS/MS): Considered the gold-standard method for the unambiguous identification and simultaneous quantification of buprenorphine and its primary metabolite norbuprenorphine. Diagnostic multiple reaction monitoring (MRM) transitions include:
Buprenorphine: $m/z$ $468.3 \rightarrow 396.2$ (loss of the $t$-butyl group and water) and $m/z$ $468.3 \rightarrow 414.2$.
Norbuprenorphine: $m/z$ $414.2 \rightarrow 340.2$ y $m/z$ $414.2 \rightarrow 101.1$.
Compliance Ratio: In biological urine toxicology, verifying compliance versus sample tampering (spiking urine directly with medication) requires measuring the norbuprenorphine-to-buprenorphine ratio; the presence of parent drug without metabolic norbuprenorphine confirms in vitro adulteration rather than ingestion.
Gas Chromatography-Mass Spectrometry (GC-MS): High boiling point and thermal sensitivity require chemical derivatization (e.g., trimethylsilylation using BSTFA or acylation) prior to analysis. Derivatized buprenorphine yields diagnostic ions at $m/z$ 450, 482, and 539 depending on the derivative employed.
Regulatory Classification & Institutional Governance
Controlled Substance Classification: In the United States, buprenorphine is classified as a Schedule III controlled substance under the Controlled Substances Act (moderate-to-low physical dependence or high psychological dependence liability, with recognized clinical uses). In the United Kingdom, it is classified as a Class C controlled drug (Schedule 3 CD under Misuse of Drugs Regulations).
Clinical Prescribing Frameworks: Historically restricted under DATA 2000 “X-waiver” requirements in the United States, prescribing regulations were modified under the Consolidated Appropriations Act of 2023 (MAT Act), allowing any clinician with standard Schedule III prescriptive authority to prescribe buprenorphine for OUD.
Institutional Security Protocols: Acquisition of pure reference standards, analytical profiling samples, or bulk active pharmaceutical ingredients mandates DEA Schedule III registration, secure vault containment, and formal chain-of-custody logging.
| Pastillas | 100, 200, 300, 400, 500, 600, 1000 |
|---|

 English English
 German
 Italian
 Dutch
 Spanish

Reseñas
Todavía no hay reseñas.